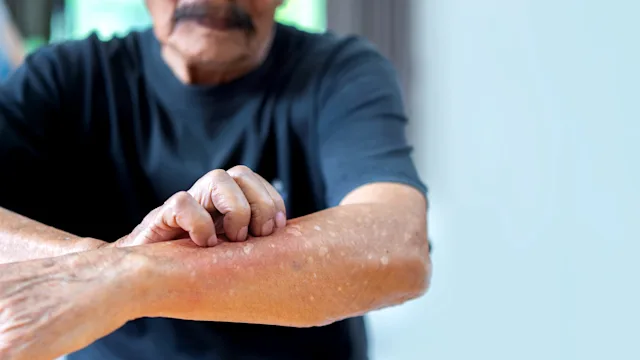
PsA is different for every person who has it. Some folks have milder symptoms. They may need less medication to feel better and protect their bodies from harm. On the other hand, some folks have very severe symptoms — like psoriasis rashes covering most of the skin or swelling and pain in most joints.
The best way to protect yourself from complications of PsA is to see a healthcare professional regularly, update them when symptoms change, and take medications as directed.
There are no specific foods to eat or avoid if you have PsA. But eating a balanced diet can help you maintain a comfortable weight, which will take pressure off of your joints. A nutritious diet can also decrease your risk of heart disease. This is important because PsA increases heart disease risk due to inflammation.
Of note, certain foods or drinks may cause psoriasis flares in some people. If certain foods or drinks worsen your psoriasis rashes, it’s a good idea to avoid them if you have PsA too.
Early signs of PsA include:
Joint pain and swelling, especially in the hands and feet
Back pain and stiffness, especially if they’re worst in the morning and get better with exercise
Sausage-like swelling of one finger or toe (dactylitis)
Psoriasis rashes
Psoriasis nail changes
If you have psoriasis and develop new joint pain, consider taking a screening test called the “PEST” (Psoriasis Epidemiology Screening Tool). The PEST helps identify people who should see a rheumatologist to be evaluated for possible PsA.
Exercise is great for psoriatic arthritis, and the American College of Rheumatology recommends it in its treatment guidelines. Keeping your joints moving will help protect flexibility and mobility, improve fatigue, and help you maintain your weight.
Walking, swimming, and cycling are good options. If walking is difficult for you due to pain, consider walking in a swimming pool instead, since the water takes weight off the joints. Yoga is also a great option since you can adjust poses for your arthritis needs.
It may be challenging to differentiate PsA from rheumatoid arthritis (RA). But with a thorough evaluation, a healthcare professional can distinguish between the two conditions.
PsA often involves the lower spine and the outer joints of the hands (distal interphalangeal joints). A history of psoriasis, nail changes, and dactylitis is more typical of PsA.
RA usually involves the neck or upper spine and other joints of the hands, wrists, and ankles. Also, it’s symmetric (similar on both sides of the body). X-rays in RA look different, with bone erosions (gradual loss of bone) being a common finding.
PsA doesn’t have a specific blood test for diagnosis. In contrast, people with RA usually test positive for rheumatoid factor and anti-CCP antibodies.
The five types of PsA are:
Oligoarticular arthritis: It involves less than five joints. This is a common type of PsA.
Polyarticular arthritis: It’s symmetric and affects five or more joints, so it can be confused with RA. Over time, most people with PsA will develop this form.
Distal arthritis: This involves mostly the joints at the tips of the fingers.
Arthritis mutilans: This causes deformities, usually in the hands and feet.
Spondyloarthritis: This involves mostly the spine.
There may be other ways to describe PsA. But this is the original and most widely used classification.
Cardiovascular disease affects most people with PsA (up to 80%). People with PsA have a more than 10% risk of cardiovascular disease within 10 years of being diagnosed. The risk is thought to increase over time due to inflammation from PsA, age, and treatments for the condition.
However, medical care for PsA has progressed, and treatments are more efficient. Earlier diagnosis and better control of PsA are now possible. As such, a recent study found that the risk of cardiovascular disease can decrease over time in PsA with effective treatment.