Polyendocrine Metabolic Ovarian Syndrome (PMOS)
Comprehensive information for you or a loved one — including treatment options and discounts on popular medications.

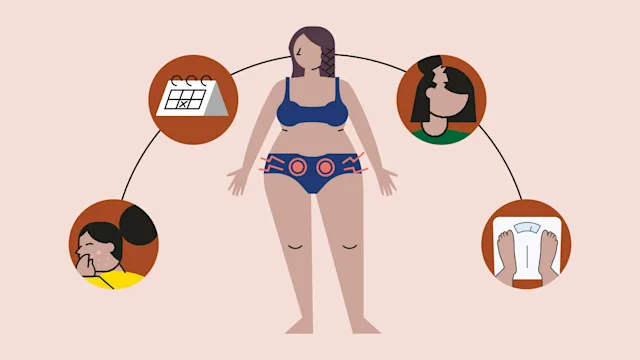
Polyendocrine metabolic ovarian syndrome (PMOS) — formerly known as polycystic ovary syndrome (PCOS) — is a hormone imbalance that affects 1 in 10 women of reproductive age. It affects different aspects of health, including:
Skin changes
Unwanted hair growth
Chronic inflammation
Metabolism changes
Also, it’s a leading cause of infertility in women.
People with PMOS usually have high levels of certain hormones called androgens. These are sometimes called “male hormones” since people with male-typical body parts make more of them. But it’s normal for female bodies to make small amounts of androgens. In PMOS, high levels of androgens (called hyperandrogenism) interfere with a healthy reproductive cycle.
Insulin is another hormone that’s usually too high in people with PMOS. Insulin helps control glucose (sugar) levels in the body. High insulin levels happen because many people with PMOS also have insulin resistance. This is a condition in which cells in the body don’t respond properly to insulin. When you have insulin resistance, your glucose levels rise, leading to prediabetes and Type 2 diabetes.
PMOS is linked with other serious health conditions, too, like high blood pressure and high cholesterol.


Experts don’t know what causes PMOS. It’s probably a combination of factors, including your genetics and environment.
PMOS can affect people of all races and ethnicities. You have a higher risk of PMOS if one of your first-degree relatives — like your mom or sister — has it. Some studies have shown that if your mother has PMOS, you are about eight times more likely to develop it. This risk increases if your mother smoked during pregnancy.
Most PMOS symptoms are caused by high levels of insulin and androgens. They can vary from person to person. Some people may have one or two symptoms, while others could have many more. Everyone is different.
These are some common symptoms people with PMOS experience:
Irregular periods (including missed periods, no periods, or very heavy periods)
Increased hair growth (called hirsutism) on the face, chest, stomach, or upper thighs
Acne that can be severe and hard to treat
Carrying excess weight (especially around the waist) or having trouble losing excess weight
Patches of thick, dark, velvety skin, usually around the neck, armpits, or genitals (called acanthosis nigricans)
Sometimes, it’s not clear if someone has PMOS, because the symptoms don’t seem related. You may be seeing different healthcare professionals for your acne and irregular periods without you or your healthcare team realizing that they’re linked.
If you think you could have PMOS, try to mention all your symptoms to your healthcare team — even if you’re not sure they could be related.
Compare prices and information on the most popular PCOS medications.
There isn’t a single test to diagnose PMOS. A healthcare professional will use a combination of your medical history and symptoms, changes on your physical exam, and (sometimes) blood work to diagnose PMOS.
A few medical organizations have developed different guidelines for diagnosing PMOS. But in general, there’s a good chance you have PMOS if other possible diagnoses have been excluded and you have at least two of the following:
Irregular periods (called ovulatory dysfunction): You have no periods, or you have infrequent periods. Typically, this means fewer than 8 cycles a year, or cycles more than 35 days apart.
High levels of androgen hormone (hyperandrogenism): You may show signs of this, like acne, male-pattern hair loss, hirsutism, and patches of thickened, dark skin. You may also have blood work to check for high androgen levels.
Small cysts on the ovaries: These are detected with an ultrasound scan (a handheld machine that uses sound waves to make images of internal organs). If you meet the first two criteria, an ultrasound isn’t needed.
The lack of a specific test for PMOS can make getting a diagnosis tricky. And the symptoms of PMOS can be similar to other conditions, like thyroid disease.
This can mean women with PMOS often struggle with symptoms for several years before getting a correct diagnosis. A study of people’s experiences getting a PMOS diagnosis found that almost half had to see three or more healthcare professionals before getting a diagnosis. One-third had a delay of 2 or more years before being diagnosed.
There’s a high risk of serious health problems linked to PMOS. Without treatment, PMOS can increase the risk of:
Weight gain: Excess weight is common with PMOS and can also raise the risk of other chronic conditions, like diabetes, high blood pressure, arthritis, and certain cancers.
Insulin resistance: The body becomes unable to use insulin properly, increasing the risk of prediabetes and Type 2 diabetes.
Type 2 diabetes: PMOS and Type 2 diabetes are both metabolic disorders that are closely linked.
Metabolic syndrome: This syndrome includes many complications, like increased body waist size, high triglycerides, and low high-density lipoprotein (HDL), the “good” cholesterol — as well as high blood pressure and impaired glucose tolerance.
Liver disease: Metabolic dysfunction-associated steatotic liver disease (MASLD) — formerly called fatty liver disease — can lead to chronic liver dysfunction and cirrhosis (scarring) over time.
Sleep apnea: Insulin resistance, weight gain, and high androgen levels can increase the risk of disordered sleep breathing.
Cholesterol abnormalities: This means unhealthy cholesterol levels (low levels of “good” cholesterol and high levels of “bad” cholesterol)
High blood pressure: High insulin levels triggering a cascade of released hormones can lead to chronic high blood pressure.
Endometrial cancer (a type of uterine cancer): People with PMOS are up to five times more likely to develop endometrial cancer.
Untreated PMOS can also increase your risk of mental health conditions, such as:
Depression and anxiety: People with PMOS are four times more likely to have depression and up to six times more likely to have anxiety.
Eating disorders: There’s a connection between eating disorders and PMOS, regardless of weight.
Finally, people with PMOS who don’t get treatment are at risk for death by suicide. If you or someone you know is struggling with self-harm, call the National Suicide Prevention Lifeline at 988, or text “HOME” to 741-741 to reach the Crisis Text Line.
Treatment for PMOS looks different for everyone, since the syndrome is a collection of symptoms that can vary from person to person. The goal of PMOS treatment is to target the various symptoms, prevent complications, and improve your quality of life.
As a first step, your healthcare team will recommend lifestyle changes — for their effects on overall health, weight, and fertility. Lifestyle changes involve:
Eating a balanced and nourishing diet
Exercising regularly
Taking steps to minimize stress
But because of the health problems related to PMOS, treatment with medication is important.
Medications to treat PMOS require a prescription from a healthcare professional.
Most medications for PMOS work by regulating hormonal imbalances. Which treatment is best for you depends on your symptoms and whether you’re trying — or not trying — to get pregnant.
Hormonal birth control is often used because it can help with many symptoms of PMOS, such as:
Regulating menstrual periods
Improving acne
Improving hair growth
Lowering the risk of endometrial cancer (cancer in the lining of the uterus)
There are many different birth control options. These include the combined oral contraceptive pill. There are also alternatives to the pill, like patches, vaginal rings, and intrauterine devices (IUDs).
These medications work by decreasing the amount of androgen your body makes and limiting androgen’s effects as well. They treat acne and hair growth associated with PMOS. Typically, these medications aren’t first-choice options. But they’re recommended if you’re unable to take the birth control pills or if the pill hasn’t worked to improve symptoms.
These are three commonly used anti-androgen medications used to treat PMOS:
Spironolactone (Aldactone)
Finasteride (Propecia)
Dutasteride (Avodart)
Weight loss can improve some PMOS symptoms in people with excess weight. Even small amounts of weight loss (5% to 15%) can improve menstrual symptoms and fertility.
Weight-loss medications typically fall into two categories:
Weight-loss pills, like Xenical (orlistat)
Glucagon-like peptide-1 (GLP-1) medications, like semaglutide (Wegovy, Ozempic) and tirzepatide (Mounjaro, Zepbound)
Many people with PMOS don’t ovulate normally, which makes it hard for them to become pregnant.
The first step to improving fertility is making lifestyle changes to optimize health and losing weight (with medication).
The next step is fertility medications. These work by helping to restore normal ovulation, improving the chances of pregnancy.
Here are some of the medications, combinations of medications, and treatments commonly used to improve fertility in PMOS. They’re listed in the order in which you’d typically try them:
Letrozole: Letrozole is the preferred first-step treatment to increase ovulation. An alternative approach is a combination of Clomid (clomiphene) and metformin (Glucophage).
Gonadotropin injections: These injections are the next step. They require office visits. They’re injections of reproductive hormones — specifically luteinizing hormone (LH) and follicle-stimulating hormone (FSH) — to stimulate the ovaries to produce eggs. Examples include Follistim AQ (follitropin beta), Gonal-f RFF (follitropin alfa), and Menopur (menotropin).
In vitro fertilization (IVF): IVF or other assisted reproductive technologies are another treatment option if first- and second-step fertility medications don’t help you get pregnant.
It can be difficult to know that you have PMOS, because the symptoms can seem unrelated and vary so much. But it’s always a good idea to see a healthcare professional if you notice:
Sudden weight gain
Irregular menstrual period
Difficulty getting pregnant
Unwanted facial hair growth
Thinning scalp hair
Skin changes
People with polyendocrine metabolic ovarian syndrome (PMOS) are almost three times more likely to develop cancer of the endometrium, which is the lining of the uterus. During a menstrual period, the endometrium is shed and removed from your body. People with PMOS have irregular periods (or no periods at all). This causes the endometrium to thicken over time, which can lead to endometrial cancer.
Whether or not there’s a link between PMOS and other types of cancer like breast or ovarian is less clear. More research is needed to better understand this.
People with polyendocrine metabolic ovarian syndrome (PMOS) are almost three times more likely to develop cancer of the endometrium, which is the lining of the uterus. During a menstrual period, the endometrium is shed and removed from your body. People with PMOS have irregular periods (or no periods at all). This causes the endometrium to thicken over time, which can lead to endometrial cancer.
Whether or not there’s a link between PMOS and other types of cancer like breast or ovarian is less clear. More research is needed to better understand this.
Some studies show that up to 80% of people with PMOS will struggle to get pregnant at some point. The good news is that it’s still possible to get pregnant when you have the condition. In fact, many are able to conceive naturally. And for those who can’t, there are good treatments available.
PMOS doesn’t go away on its own, and there’s no cure. But lifestyle changes that prioritize your health along with medications can help manage the symptoms and prevent long-term health complications of PMOS.
Additional treatment options for excess hair growth in PMOS are available. Here are some to consider:
Electrolysis: A small needle is used to destroy hair follicles with a pulse of electric current. The results are usually permanent, but multiple treatments are needed.
Laser treatment: This destroys hair follicles with heat. The results are usually permanent, but several treatments are needed.
Eflornithine hydrochloride (Vaniqa): This is a prescription cream that makes facial hair less coarse and visible over time.
American College of Obstetricians and Gynecologists. (2026). Endometrial hyperplasia.
Bhat, Y. J., et al. (2020). Laser treatment in hirsutism: An update. Dermatology Practical & Conceptual.

Prescription savings
Stop paying too much for your prescriptions. Compare prices, get pharmacy coupons, and save up to 80%. Find expert answers to your health questions so you can make the best decisions for yourself and your family.
Health conditions
Medications & treatment
Access & affordability
Medication discounts